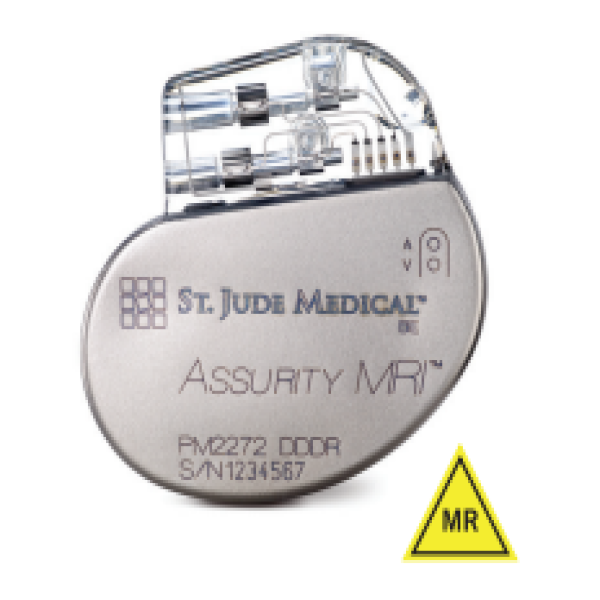
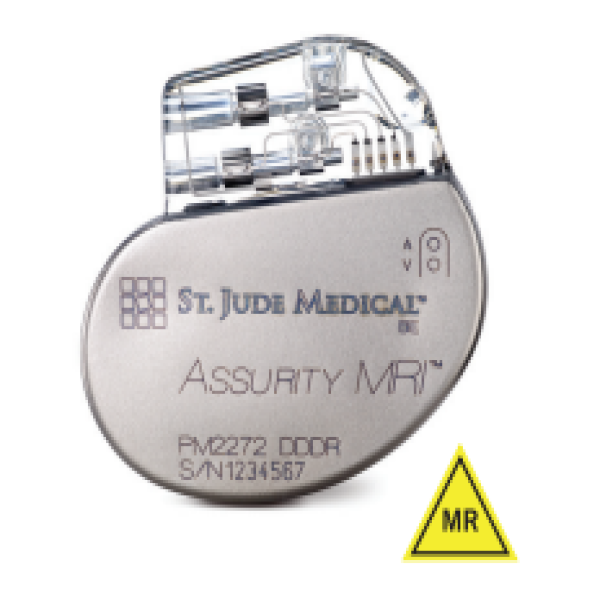
Assurity MRI™ Dual-Chamber Pacemaker
- When combined with the Tendril MRI™ LPA1200M lead, the MRI-ready device:
- – Allows full-body, MRI scans*
- – Permits a maximum whole body averaged specific absorption rate (SAR) of 4 Watts per kilogram (W/kg) n When combined with the Tendril™ 2088 or IsoFlex™ Optim™ 1944/1948 leads, the MRI-ready device:
- – Allows MRI scans*
- – Permits a maximum whole body averaged specific absorption rate (SAR) of 2 Watts per kilogram (W/kg)
Call Us Now
Product Highlights - Pacemaker
The Assurity MRI pacemaker was designed to allow patients to undergo MRI scans:
- When combined with the Tendril MRI™ LPA1200M lead, the MRI-ready device:
- – Allows full-body, MRI scans*
- – Permits a maximum whole body averaged specific absorption rate (SAR) of 4 Watts per kilogram (W/kg) n When combined with the Tendril™ 2088 or IsoFlex™ Optim™ 1944/1948 leads, the MRI-ready device:
- – Allows MRI scans*
- – Permits a maximum whole body averaged specific absorption rate (SAR) of 2 Watts per kilogram (W/kg)
- An optional, easy-to-use hand-held device (SJM MRI Activator™ device) can be used to program the device to pre-approved MRI settings pre- and post-MRI scan, decreasing the number of workflow steps and increasing clinic efficiency
- Physician preferred size and physiologic shape minimize pocket size n Outstanding longevity provides 9,4 years of service life,7 which is supported by an 8-year warranty8
- InvisiLink™ wireless telemetry, in conjunction with the Merlin@home™ transmitter and Merlin.net™ Patient Care Network (PCN), allows for daily remote monitoring and follow-up
- CorVue™ congestion monitoring offers greater insight into pulmonary edema status by monitoring transthoracic impedance, and it provides the option for both patient and physician alerts
- The only pacemaker with programmable AT/AF alerts specifically indicated for detecting atrial tachyarrhythmias, which have been found to be associated with an increased risk of stroke in elderly, hypertensive, pacemaker patients without prior history of AF12
- A suite of state-of-the-art features—complete automaticity (atrial and ventricular), Ventricular Intrinsic Preference (VIP™) technology, the AF Suppression™ algorithm and SenseAbility™ technology—is designed to deliver optimal therapy for patients at implant and throughout their lives
- 6-month ERI-EOL interval
Indications: Implantation is indicated in one or more of the following permanent conditions: syncope,
presyncope, fatigue, disorientation due to arrhythmia/bradycardia or any combination of those symptoms.
Rate-Modulated Pacing is indicated for patients with chronotropic incompetence, and for those who would
benefit from increased stimulation rates concurrent with physical activity. Dual-Chamber Pacing is indicated
for those patients exhibiting: sick sinus syndrome, chronic, symptomatic second- and third-degree AV
block, recurrent Adams-Stokes syndrome, symptomatic bilateral bundle branch block when tachyarrhythmia
and other causes have been ruled out. Atrial Pacing is indicated for patients with sinus node dysfunction
and normal AV and intraventricular conduction systems. Ventricular Pacing is indicated for patients
with significant bradycardia and normal sinus rhythm with only rare episodes of A-V block or sinus arrest,
chronic atrial fibrillation, severe physical disability. AF Suppression algorithm is indicated for suppression
of paroxysmal or persistent atrial fibrillation episodes in patients with one or more of the above pacing
indications.
Contraindications: Dual-chamber pulse generators are contraindicated in patients with an implanted
cardioverter-defibrillator. Rate-Adaptive Pacing may be inappropriate for patients who experience angina
or other symptoms of myocardial dysfunction at higher sensor-driven rates. An appropriate Maximum Sensor
Rate should be selected based on assessment of the highest stimulation rate tolerated by the patient.
AF Suppression™ stimulation is not recommended in patients who cannot tolerate high atrial-rate
stimulation. Dual-Chamber Pacing, though not contraindicated for patients with chronic atrial flutter,
chronic atrial fibrillation, or silent atria, may provide no benefit beyond that of single-chamber pacing in such
patients. Single-Chamber Ventricular Demand Pacing is relatively contraindicated in patients who have
demonstrated pacemaker syndrome, have retrograde VA conduction, or suffer a drop in arterial blood pressure
with the onset of ventricular pacing. Single-Chamber Atrial Pacing is relatively contraindicated in patients
who have demonstrated compromise of AV conduction.
Potential Adverse Events: The following are potential complications associated with the use of any pacing
system: arrhythmia, heart block, thrombosis, threshold elevation, valve damage, pneumothorax, myopotential
sensing, vessel damage, air embolism, body rejection phenomena, cardiac tamponade or perforation,
formation of fibrotic tissue/local tissue reaction, inability to interrogate or program a device because of
programmer malfunction, infection, interruption of desired device function due to electrical interference,
loss of desired pacing and/or sensing due to lead displacement, body reaction at electrode interface or
lead malfunction (fracture or damage to insulation), loss of normal device function due to battery failure or
component malfunction, device migration, pocket erosion or hematoma, pectoral muscle stimulation, phrenic
nerve or diaphragmatic stimulation. The following, in addition to the above, are potential complications
associated with the use of rate-modulated pacing systems: inappropriate, rapid pacing rates due to sensor
failure or to the detection of signals other than patient activity, loss of activity-response due to sensor failure,
palpitations with high-rate pacing.
Refer to the User’s Manual for detailed indications, contraindications, warnings, precautions and potential
adverse events.